Showing posts with label provider leverage. Show all posts

Provider Clout

There have been a few excellent articles and studies on provider consolidation – and how much this impacts the overall costs of health care costs.

Kaiser Health News and NPR aired a 7 minute piece on Saturday demonstrating the impact of Sutter Health System in northern California.  It’s almost impossible for major insurance companies to sell policies for products that don’t include Sutter, which receives reimbursement that is now 37% higher than other providers in the area.   Sutter has a profit margin of over 17% - far out of line with most profit or nonprofit hospital systems across the country.  An insurance broker demonstrated that a small business with 20 employees could save $120,000 per year by purchasing health insurance that did not include Sutter.  But he can find few takers for this type of limited network.
Click to enlarge image


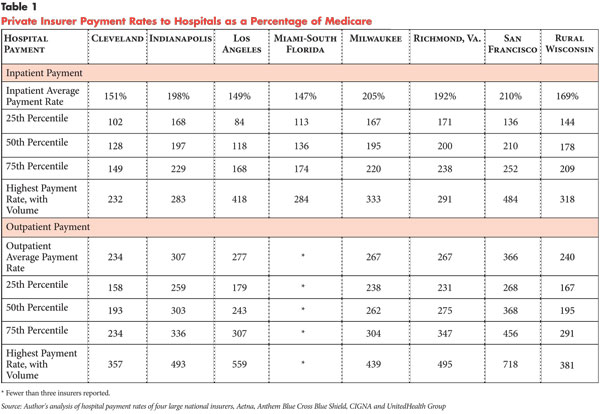
The Center for the Study of Health System Change published a study of 8 markets (including northern and southern California) showing that four large national health insurers pay hugely variable amounts for the health care they provide to their members.  In Los Angeles, the average commercial (employer-sponsored) health plan pays 118% of Medicare for inpatient care.  However, the 25%ile hospital receives 84% of Medicare payment, the 75%ile hospital receives 168% of Medicare, and the highest paid hospital receives over four times Medicare payment. 


The Boston Globe  noted last week that Massachusetts Attorney General Martha Coakley has promised to revisit the issue of provider market clout, worrying that proposed payment reform is not enough.  However, as the Center for Health System Change noted, once there are widely different allowed charges among facilities, it will be very hard indeed to roll these back.

The New York Times published an article today noting increasing consolidation of hospitals, ambulatory care centers and physicians.  The article outlines the fear that as providers establish accountable care organizations to service Medicare under health care reform, their influence will grow even larger, as will their ability to extract high prices.


Click to enlarge image

OK – that’s the doom and gloom.  In our class last week, we saw a graphic showing that hospitals have MUCH less consolidation (at least according the US census bureau) than health insurers.  Physicians have less consolidation than just about everyone except for florists.  So- this means there is no problem, right?

Wrong!

Health care delivery is hyperlocal.    Sutter has very high prices and very high margins, and Sutter has high market penetration and importance in its limited geography. It doesn't matter that Sutter provides under 1% of all health care delivery in the US, while  United HealthCare is responsible for insuring 70 million Americans.  In Northern California, Sutter has far greater dominance than any health plan, and is able to use that to drive very high prices.  Limited or tiered networks can exert at least some downward pressure on these prices. 

California Provider Leverage Drives Health Care Cost Increases

I blogged yesterday about health plan powerlessness to control cost per unit – the major driver of excess health care costs in the US compared to other developed OECD countries. 


As if on cue, Health Affairs published an article from the Center for Health System Change pointing out that this is exactly what has happened in California.  A combination of public demand for full provider choice and consolidation of hospitals and physicians has left health plans with little power to control overall costs.

A direct quote:

“Physician overlap in two prominent health plan networks was 9798 percent. This reality weakens the position of health plans. If plans cannot exclude providers from their network because of customersdemands for broad networks, they cannot credibly threaten network exclusion. That fact undermines their ability to resist providersdemands for higher payment rates.


Although it doesn’t seem possible that prices could have increased even faster, it turns out that providers sometimes don’t wield all available leverage power in negotiations. In effect, they leave “money on the table” because
-          Hospitals and big physician groups worry that raising prices too high will chase business away from the local geography
-          Hospitals and big physician groups worry that raising prices for smaller health plans might increase health plan concentration
-          Kaiser Permanente in Northern California has large market presence and drives costs down in that market.


I am convinced that more integration of provider groups can lead to higher quality of care – and more cost-effectiveness, too.   This quote from a physician who had moved from Fresno, a non-integrated market, gives me pause:

The good thing about the systems not being highly integrated and coordinated [in Fresno] is that premiums are lower. Why are those hospitals and physicians [integrating]? It wasnt for increased coordination of care, disease management, blah, blah, blahthat was not the primary reason. They wanted more money and market share.

Many observers have commented on the importance of vigorous enforcement of antitrust regulations.  However, this article points out that some characteristics that make a hospital a “must have,” high-leverage facility, such as reputation and provision of unique services, are not addressed by antitrust enforcement. 

The authors conclude that policy makers should consider price caps and all-payer rate setting.  Of course, all-payer rate setting would likely require Medicare and Medicaid to pay substantially higher rates.  Since Medicare is already woefully underfunded and the states are chafing at Medicaid costs, no one will be enthusiastic about an approach which increases Medicare and Medicaid liabilities.

The market helped control prices when hospitals and care delivery systems genuinely competed against each other. In the current environment, where health plans must have a contract with all providers, hospitals (and delivery networks) have become akin to utilities. Utilities are usually subject to price regulation.