Showing posts with label Massachusetts. Show all posts

More Good News from Massachusetts

Today’s Managing Health Care Costs Indicator is $453 Million

The blogosphere has focused a lot of attention on Massachusetts, where almost everyone (97+%) has health insurance as a result of health care reform that looks almost exactly like the Affordable Care Act.  Our costs in this state are exceptionally high – although they are rising more slowly than costs in other states.

A study released last week by the Massachusetts Taxpayer Foundation  – a nonpartisan group that advocates for good government (including promoting prudence in spending) – shows that it cost the state an additional $453 million, or  an incremental $91 million on the average for each of the last five years to extend coverage to another 7.6% of the population.   The total cost was a bit over $900 million –the additional amount was spent by the federal government for Medicaid and waivers,  employers who increased the portion of the population insured during this time period despite the recession, and individuals who purchased insurance and who would have otherwise gone “naked.”

It’s not perfect for states to go this alone.  Massachusetts hospitals on the New Hampshire border are already seeing higher rates of bad debt due to the difficulty of obtaining affordable insurance to the north.

And the total dollars being spent are not inconsequential.    However, incremental spending to support expanded coverage is equivalent to 1.4% of the total state budget. Seems like a good deal.

We’re Number One


Today’s Managing Health Care Costs Indicator is One

Click on image to enlarge.   Source 
 The eyes of the nation have been focused on Massachusetts, as the Affordable Care Act is modeled on health care reform in Massachusetts.  When it comes to cost, We’re Number One!

The Blue Cross Blue Shield of Massachusetts Foundation just published a great 50-slide deck of graphics comparing  health care cost and utilization in Massachusetts with the rest of the country.  Massachusetts has the highest cost of health care in the country, and the largest number of physicians per capita.   Our physicians are more likely to be specialists than in the rest of the country.   Our hospitals are more than twice as likely to be academic medical centers.   Our health insurance designs are among the richest around, with low average deductibles.

Most of the increased cost of care since Massachusetts’s health care reform has been cost per unit, not increased utilization.   The rate of cost increase in Massachusetts has been lower than the rest of the country since we passed our health care reform, although of course we started at a much higher base.

Implications of Massachusetts experience for the post-ACA American health care system:
·      Increasing access doesn’t lead to an instant onslaught of new utilization
·      Health care is regional –and structural issues (not health care reform) make health care in Massachusetts spectacularly expensive
·      We need to keep our eyes on price – not just utilization – if we want to control the rate of health care inflation
*  Health care inflation crowds out other important societal priorities (see graphic at the bottom of this post.   That's why health care reform, and control of health care costs are so important. 

The  Blue Cross Blue Shield Foundation conclusions:

  • Massachusetts spends more on health care than any other state.
  • Higher costs were not caused or markedly accelerated by health reform, as Massachusetts has been a high spending state for years.
  • The underlying difference in spending between Massachusetts and the U.S. overall is rooted in the state’s demographics, insurance coverage, and health care market structure, which includes disproportionately many specialists and teaching hospitals and some very large and powerful hospital systems.
  • Though the amount of most services used increases every year, the majority of the growth in health spending comes from increased prices.
  • There is enormous variation in total health care spending across the state, stemming from variations in both price and utilization.
  • However, neither higher prices nor higher utilization of services is associated with higher quality or better health outcomes, suggesting that there is a significant amount of waste in the Massachusetts health care system. It also suggests that costs can be lowered without decreasing overall quality or health outcomes.
Click image to enlarge. Source 

Day Six of Good News: Massachusetts


Today’s Managing Health Care Costs Indicator is 2%


If you watch the Republican Presidential debates, you’d guess that the health care system in Massachusetts was in utter disarray.   Mitt Romney at least intermittently runs away from what’s probably the signature effort of his one-term governorship, and Newt Gingrich and others rarely go a day without throwing mud and bombs.

Here in Massachusetts, things are… much better than you might think.
  • Our rate of uninsured is about 2% - the lowest in the nation
  • Our current rate of health care cost inflation is no longer the highest in the nation, although it’s still far too high
  • There has been a dramatic move toward contracts that include global payments, which will likely mean that providers will play an important role in modulating future health care cost increases
  • The Attorney General has published meaningful cost data that has been risk adjusted.
  • The state just renegotiated its Medicaid waiver, allowing continued funding for subsidies for health care coverage for the poor and near poor.


Massachusetts’ health care reform was clearly a model for the Affordable Care Act. It’s working well here –which augers well for the future of health care in the US.

I wish all a Happy New Year –and I’ll have some 2011 wrapup and health care innovations that could lower cost from my HSPH fall course “Managing Health Care Costs” over the next week.


The Stakeholders Would Just Plotz!


There’s been some jubiliation in Massachusetts with the Commonwealth Fund report that insurance here is no longer the most expensive in the country.  My colleague Nancy Turnbull, has a great post in the Commonhealth Blog entitled “Stop Kvelling, We Still Need Aggressive Action To Halt Rising Premiums.”  She points out that any jubilation is misplaced – our health care premiums have gone up rapidly – just not as rapidly as a handful of other states.  In fact, by many measures our health insurance remains the most expensive in the country – which means the most expensive on the planet.  

The problem, of course, is that halting the rise of health care premiums will create hardship in the state’s growth industry – health care.  In fact, most of the proposals to lower health care costs make the stakeholders want to plotz!

The commentary is great - and it’s topped off by a prolonged metaphor that left me chuckling. Nancy’s response to a question about why politicians don’t address the impact of rising  health care costs on small business:

There's clearly a great fear of "killing the golden goose" of health care in Massachusetts.  The problem is that the golden eggs are not distributed fairly although we're all paying for the feed, and the price of over-feeding the goose is a starvation diet for  others (including public health).  Sort of like the health care equivalent of foie gras.


(Kvell is a great Yiddish word that means something approaching gloating –but it’s virtuous. We kvell when our kids make deans list.  Plotz is to be so annoyed that you could faint with anger.  When someone threatens to take away what’s mine, I could just plotz.

Three Graphs Tell the Story: It's the Prices!

These three graphs are from the Recommendations of the Massachusetts Special Commission on Provider Price Reform. released last week.  For anyone who wonders if unit cost is a substantial portion of the cause of health care cost increase in Massachusetts, these data paint a clear picture.

The entire report can be accessed at this link.


Click on any image to enlarge it.


Jon Kingsdale, the founding Executive Director of the Connector Authority in Massachusetts, will be talking about the role of government in health care costs in our HSPH course on Wednesday.  Here's a link to a Health Affairs blog post of his from July on the problem of "costitis."

Physician Group Lowers Cost While Improving Quality


Today’s Managing Health Care Cost Indicator is $16,000

Click image to enlarge.  Source

November’s Atlantic Monthly profiles Caremore, the California-based physician practice purchased this spring for $800 million by Wellpoint, the nation’s largest health insurance plan.  The practice cares for about 50,000 Medicare beneficiaries, and is paid through capitation via the Medicare Advantage (Part C) program.

The practice is about 20 years old, and has an impressive record of improving care while lowering overall costs.  Much of what the practice does is invest in improved care – by paying for taxi rides, doing home visits to assess risks of falls, seeing diabetics with small foot injuries every few days, and electronic monitoring of those at risk for hospitalization from congestive heart failure.

The article is heartening – the practice appears to be doing well by doing good.  These techniques have been used by groups paid capitation by Medicare for years – I remember our group in Cambridge setting up home physical therapy visits to do assessment for fall risks in the early 1990s.   Wellpoint’s purchase of this group (at an eye-popping $16,000 per patient) is market validation that this model works to improve quality and lower cost for the elderly.  Some of these lessons are applicable to those under 65, although there are far fewer very sick people in the younger population who would benefit from many of these approaches.  For instance, 30 day hospital readmission rates are 20% in the Medicare population, but only 9% for a privately insured younger population.  Remember that many of these readmissions are for planned chemotherapy or staged surgery, too.

This provides a good example that providers given a budget can manage to make health care more affordable.   That’s good news for policymakers in Massachusetts, who are pushing toward legislation to expand global payment to control health care costs.  However, expanding this approach from a niche group of providers to an entire state will be no small challenge.

Dueling Estimates of Cost Saving From New Massachusetts Blue Cross Global Payment Contract


Today’s Managing Health Care Costs Indicator is $15.51. 
Or Maybe it’s -$70.20


Click to enlarge

The New England Journal of Medicine published an financial assessment of the first year of the Blue Cross Blue Shield of Massachusetts Alternative Quality Contract last night. It’s been making the headlines for showing that groups in this contract, which includes provider responsibility for overall financial costs, had lower overall increase in medical claims spending than groups that were not in this contract.

The headlines have been clear.  “It saves money”  You have to read well into the coverage  to see that this isn’t accurate.

The authors of the NEJM article are very clear that the AQC did not save money in the first year, which is consistent with last month’s report from the Massachusetts Attorney General.  In fact, the authors state:

Total BCBS payments to AQC groups, including bonuses for quality, are likely to have exceeded the estimated savings in year 1.

The combination of bonuses for being below budget (~3%) and bonuses for achieving quality thresholds (3-5%) and extra BCBSMA administrative costs (0-2%) made the AQC groups substantially more expensive than non-AQC groups.  The AG report showed clearly that early adopter AQC groups had surprisingly high total costs in the Blue Cross plan – probably because of these additional expenses.  (The $70.20 above is multiplying the AG medical inflation differential by the calculated quarterly cost from the NEJM article referenced above)

Another surprise is that in the medical claims costs, we aren’t seeing evidence of better quality of care such as fewer admissions or emergency department visits. Utilization changes are not different between AQC and non-AQC groups. Rather, the AQC groups referred patients to less expensive providers – so the lower claims cost was entirely from lower unit costs.   

Note also that the analysis excluded pharmacy. The AQC groups might well have had higher pharmacy costs, since the physicians received bonuses based on hitting some quality measures that require prescription medications.

It’s not a surprise that BCBSMA had to pay a lot to entice groups to join this capitated program – and no one should have expected lower costs in year one .  I’m hopeful that over time this program will yield lower costs – because physicians in a global payment arrangement figure out how to save resources.  

However, the AQC is like many other medical management interventions in that right now BCBSMA can only claim that its AQC has improved quality – not that it has lowered cost.  

Premium Freeze in Massachusetts?


Today’s Managing Health Care Costs Indicator is 0


Health Care for All, an advocacy group that played a substantive role in passing health care reform here in Massachusetts, has come out in favor of a health insurance premium freeze.    They cite the case of Sarah Higginbotham, who says her biweekly take-home pay for a part time job at a church used to be $900, but has dwindled to $164 since she now has a family plan and health insurance premiums have risen by double digits each year.

Premium increases are caused by a combination of increased unit prices, increased utilization, increased intensity of services, and increased burden of illness.  Price increases could be substantially decreased or eliminated quickly, although that might take price controls.   Lifestyle change can lower burden of illness, but not by 2012.  Increased utilization can be changed – but takes some time.  Increased intensity of service sometimes represents innovations that can save lives (such as today's New England Journal, which has an article showing that screening CT scans for those at high risk for lung cancer can save lives. More on that in a future post.)  


Most insurance funded by large insurers is “self insured,” so that the stated premium is irrelevant – as the employer pays the bills.  However, smaller employers need to purchase “fully funded” insurance –so the level of stated premium is the price paid by the employer and employee.   A premium freeze would be a big break for small employers and nonprofits.   But it won’t be easy to achieve, and lower premium increases will only be sustainable with genuine change in the health care delivery system.

Health insurers in Massachusetts could offer a premium freeze on fully-insured health plans by one of the following methods:


Lower Profits:
Some insurers have high profit margins, and could endure a year of a premium freeze just be accepting lower profits.  However, Massachusetts insurers generally have low profit margins.


Lower administrative costs:
Administrative costs for the nonprofit regional health plans here are also on the low side nationally.   Administrative costs represent less than 10% of total premium, and the claims must be paid – so that wouldn’t likely achieve enough savings to allow for a premium freeze.


Lower provider payments The Attorney General’s report documents that some providers receive higher unit payments, and also have higher risk-adjusted total medical expense costs.  However, each health plan would need to reopen negotiations with multiple providers to get lower prices.  The market has determined those prices – so it won’t be easy to change these quickly.  Remember also that we don’t have providers with huge profit margins. So, significant provider pay cuts will likely cause job loss and attempts to cost-shift to payers that have less leverage.


 Lower medical costs Health plans have been performing medical management for years – and these programs can make a difference, especially for high risk patients.  Health management programs aren’t cheap, though, and they take a substantial amount of time to pay off.   I don’t imagine that plans to increase medical management or to improve healthy lifestyles of Massachusetts residents will make huge difference in health care costs in 2012.


Cost-shifting Insurers could raise premiums elsewhere to cover the lost revenue from a premium freeze.  Again, the market wouldn’t make this easy – and some national insurers might leave the state.


Risk-shifting Insurers could avoid insuring the sickest patients – and could therefore avoid premium increases.  However, regulation of the small group market makes it difficult for health plans to selectively enroll healthy patients.

So, I’m not optimistic we’ll achieve a health insurance premium freeze in Massachusetts in 2012.  However, hats off to Health Care for All for humanizing the impact of health care premium increases.   I think this conversation can help push meaningful change in health care delivery that could lower future health care cost increases.

RomneyCare Works.


Today’s Managing Health Care Costs Indicator is 98.1%

Click to enlarge image
There has been a lot in the national press about how health care reform in Massachusetts has worked.  There's a lot of blather on both sides of the political spectrum, and the Boston Globe had a comprehensive article today reviewing how “RomneyCare” is working here. 

Conclusions:

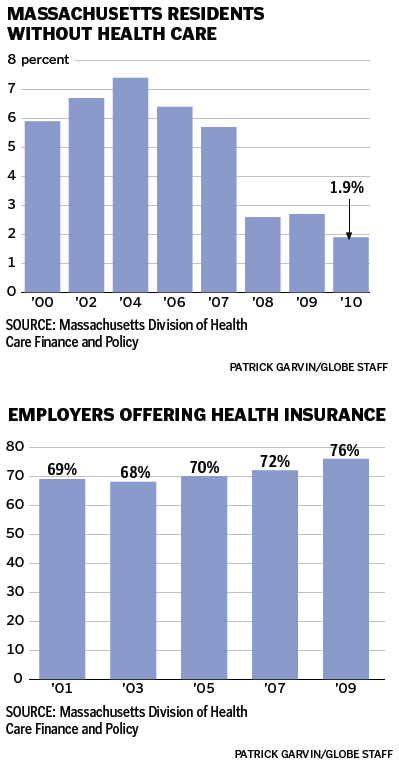
1) Far more people are insured than before health care reform, despite the disastrous recession (98.1%)
2) More employers (up from 70 to 76%) are offering insurance, again despite the recession
3) The exchanges work for individuals - they haven't worked well for small employers yet
4) The cost of the care of the uninsured has declined.
5) There is inadequate primary care access, and ED visits have gone up rather than down.
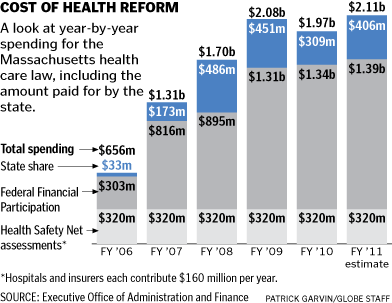
6) The cost has been manageable - but the state has relied on some payments from the feds (stimulus dollars and Medicaid add-on dollars) that will not continue. The federal government has paid a disproportionate share of the total cost (as it will under the Affordable Care Act).
7) Health care reform promised incremental provider Medicaid payments that have not been funded. Hospitals say they must pass these costs on to other payers, which worries employers greatly.
8) Health care reform is actually pretty popular in Massachusetts.  The last Harvard School of Public Health poll said that 63% of residents support health care reform. 


Massachusetts’ Health Care Reform: Chapter 2


Today’s Managing Health Care Costs Indicator is 52

  
Governor Deval Patrick of Massachusetts announced the state’s plans to move from fee for service to bundled payments for accountable care organizations (ACOs) last week.   The initiative could be a bold reshaping of health care in the Commonwealth It could be the opening volley in a battle to reintroduce rate regulation.  Or it could be an interesting idea that doesn’t make any legislative headway. 

Here’s my outline of the 52 page proposed legislation

·      * The Attorney General is instructed to:
o   Evaluate potential provider mergers and accountable care organizations (ACOs) to be sure these are not anticompetitive
o   Help arrange necessary federal waivers
o   Develop an enforcement mechanism to prohibit providers from shifting costs from one payer to another.
·      * The Division of Insurance will
o   Collect data on provider contracts and determine if they are consistent with legislation, including increases below certain thresholds.
o   Disapprove rate hikes that are based on provider contracts inconsistent with this legislation
·      * The Executive Office of Health and Human Services will
o   Help arrange necessary waivers
o   Establish an ACO pilot with early-adopter provider organizations
o   Report on progress
·      * The Division of Health Care Finance and Policy (DHCFP) gets substantial new responsibilities:
o   Evaluate alternative payment methods
o   Determine how to share reporting on payments with the public
o   Examine terms of health plan contracts with providers, and require annual reporting on these, including an inventory of payment methods to be completed by March, 2012
o   Figure out how to apply the state’s preferred payment methodology to self-funded employers
o   Study best practices from other states and other countries
·      * Establishes a Health System and Payment Reform Coordinating Council with responsibilities including:
o   Collects data and report on quality and cost
o   Determines what entities qualify as an ACO
o   Monitors and reports on ACO performance
·      *Establishes a Health Care Information Technology Council and a Behavioral Health Task Force
·      *Mandates that primary care physicians participate in only a single ACO
·      *Establishes a mandatory self-funding reinsurance plan for ACOs 
·      *Standardizes and enforcesuniform risk adjustment so that ACOs and health plans will not “win” by failing to serve those with serious illness.
o   Risk adjustment is supposed to include socioeconomic status, which is notoriously difficult
·      *Malpractice reforms include
o   “Cooling off” period before malpractice claims can be filed, to allow for settlement talks.
o   Disallows apologies from being used against providers in malpractice claims.
o   Protects peer review privilege within ACOs


This is a big bill – and will be changed significantly as it winds its way through the legislative process.

Here are some key observations about factors which will determine this bill’s success.

  •  There are many new responsibilities, especially for DHCFP.   Will there be staff to complete these requirements? Will there be adequate budget to hire independent actuaries and analysts for what the department cannot do within its own staff?
  • Providers and health plans feel proprietary about their contractual arrangements, and have spent years developing the expertise to maximize returns.  The contracts are complex and often not easily comparable
  • It isn’t easy to compare provider prices
    • It’s easiest to compare cost using relative discount rates.  But the ‘chargemaster’ used by most providers is hopelessly irrational.
    • It’s also possible to compare charges for high volume units of service (such as medium intensity office visits.) 
    • However, it’s more appropriate to compare the cost of risk-adjusted episodes of care, so that the provider who uses more units of service doesn’t inappropriately appear to be offering a better “deal.” 
    • Risk adjusting episodes of care is doable- but it’s not for the faint of heart.
  •  The current bill appears to target rate of increase, which would not address existing disparities in allowable fee schedules.
  • A substantial portion of Massachusetts residents get coverage through ERISA eligible plans, where an employer self-funds the health insurance benefit.  These plans are not subject to Massachusetts regulations.   If these plans continue to be fully committed to fee for service, it might be hard to get traction with the provider community
    • On the other hand, Patrick has announced that he expects full participation of 1.7 million beneficiaries who have state-funded health care (state employees, many municipal employees, and Medicaid recipients).


This proposed legislation is ambitious and groundbreaking – a fitting followup to the health care reform that has led to insurance coverage for 98% of Massachusetts residents.